
Why the Pilot Working Isn’t the Same as the Pilot Scaling
You ran the pilot. Clinicians liked it, or tolerated it. The demo to the board went fine. Now someone asks: can we roll this out to the other four units, or the other two hospitals in the system?
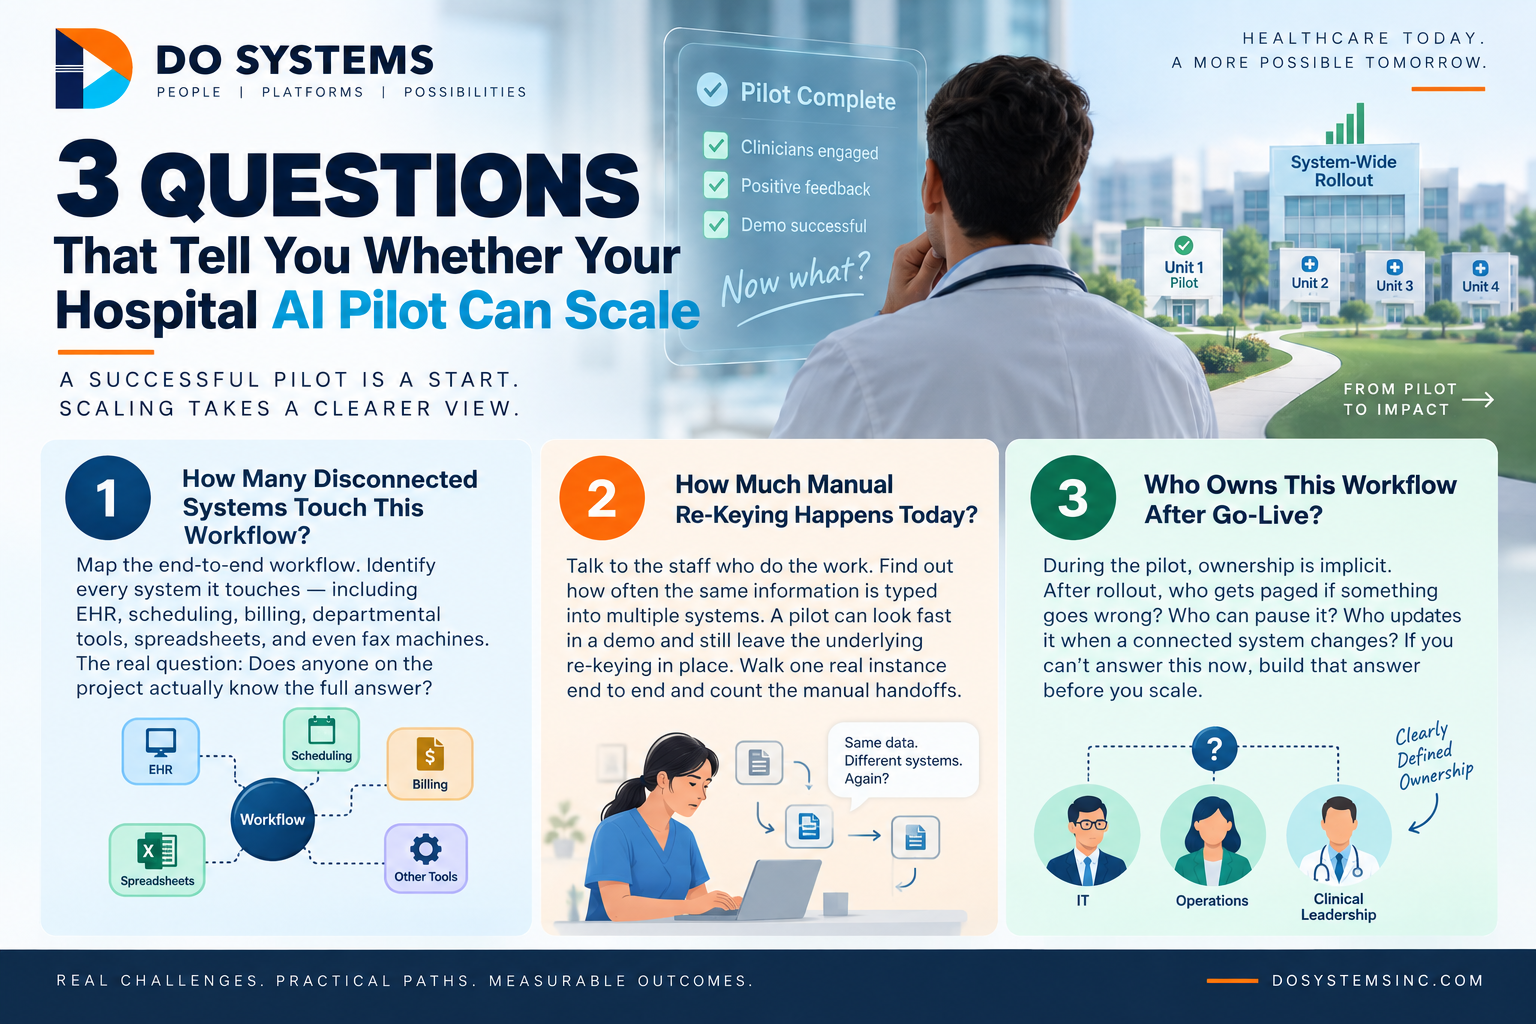
That’s a different question than “did the pilot work.” A pilot can succeed in a controlled unit with a motivated team and still fail to scale, because scaling exposes everything the pilot let you ignore: the systems it didn’t touch, the re-keying it didn’t eliminate, and the fact that nobody was formally responsible for the workflow once the project team moved on.
Before you approve budget for phase two, ask three questions. They won’t predict success. No single assessment can, and we’re not going to pretend a 10-point checklist produces a score that guarantees an outcome. What these questions do is force a conversation that most pilot teams skip.
Question 1: How Many Disconnected Systems Touch This Workflow?
Start by mapping the workflow the pilot automated or assisted — not the tool, the workflow. Intake, triage, discharge planning, prior authorization, whatever it is. Count every system that workflow currently touches: the EHR, a scheduling tool, a billing platform, a departmental spreadsheet, a fax machine that’s technically still in production.
In a lot of hospital environments, this number is higher than the org chart suggests, because shadow IT fills gaps that IT never signed off on. A unit adopts a scheduling app because the enterprise one doesn’t fit their workflow. A team keeps a shared spreadsheet because two systems don’t talk to each other. None of that shows up in the architecture diagram, but all of it touches the workflow you’re about to scale.
The question to ask isn’t “how many systems is that, exactly” as a pass/fail test. It’s: does anyone on this project actually know the answer? If the honest answer is “we’re not sure,” that’s the finding. Scaling a pilot into an environment you haven’t fully mapped is how integration problems that were invisible in one unit become visible, expensive, and public in five.
Question 2: How Much Manual Re-Keying Happens Today?
The second question is about the humans in the workflow, not the systems. Ask the staff who actually do the work: how often do you type the same information into a second system because the first one doesn’t pass it along?
This is different from asking whether the pilot “saved time.” A pilot can look fast in a demo and still leave the underlying re-keying in place — the AI layer just adds a step on top of the manual one instead of replacing it. Staff will tell you this directly if you ask them specifically about re-keying, rather than asking the general “did this help” question, which people tend to answer politely.
Walk one instance of the workflow end to end with the person who does it daily. Count the manual handoffs. That number tells you where the pilot’s real work is: not the AI model, but the integration and workflow redesign around it. A tool that reduces clinical decision time by a few minutes but leaves three manual re-entry steps in place hasn’t fixed the workflow. It’s added to it.
Question 3: Who Owns This Workflow After Go-Live?
The third question is organizational, and it’s the one pilot teams avoid because the honest answer is often “nobody, yet.”
During a pilot, ownership is implicit. The project team is watching, the vendor is on standby, IT is monitoring closely because it’s new. Six months after rollout, none of that is guaranteed. If a workflow starts producing bad outputs, missing data, or a spike in exceptions, who gets paged? Who has the authority to pause it? Who updates the process when a connected system changes its data format?
This question connects directly back to the first two. Unclear ownership is often exactly what let shadow IT tools and disconnected systems creep into the workflow unnoticed in the first place — nobody was watching the whole picture, so each team solved its own gap locally. If nobody owns the workflow end to end, the disconnected systems and the manual re-keying don’t get fixed. They just get inherited by whoever notices next.
If you can’t answer who owns the workflow after go-live, that’s not a reason to cancel the pilot. It’s a reason to build that answer before you scale it, not after something breaks in production.
What These Three Questions Don’t Tell You
We want to be direct about the limits here. These three questions are diagnostic prompts, not a scoring model. We’re not going to tell you that hospitals typically have a certain number of disconnected systems, or that a certain percentage of re-keying is normal, because we don’t have data to back that up and neither does anyone else who says they do with a straight face. Be skeptical of any assessment that hands you a benchmark number without showing you where it came from.
What the questions do is put a system integration problem and a workflow-ownership problem on the table before they become a rollout problem. That’s the entire point of asking them before you scale, not after.
Ten Questions, Not Three
These three questions are a starting point, not the whole assessment. A full readiness review also looks at data quality, staff training load, vendor integration commitments, and how the workflow will be monitored after launch — the areas that don’t show up until you’re several months into a rollout.
If these three questions raised more uncertainty than you expected about the systems, re-keying, or ownership behind your pilot, work through the full picture before you commit rollout budget. Download the AI Readiness Checklist, a 10-point walkthrough built for operations and IT leads to run together, and see where the gaps actually are.
AI Readiness Checklist (10 points)
FAQ
What is an AI readiness assessment for a hospital?
It’s a structured review of the systems, workflows, and ownership around a process before you scale an AI pilot into it — not a score, but a set of questions that surface integration gaps, manual workarounds, and unclear accountability before they become production problems.
Why do hospital AI pilots that work in one unit fail to scale to others?
Pilots often succeed because a motivated team compensates for gaps a broader rollout can’t sustain — disconnected systems the pilot didn’t touch, manual re-keying the pilot didn’t eliminate, and no formal owner once the project team moves on.
Do these three questions guarantee a pilot will scale successfully?
No. They’re diagnostic questions to have before you commit budget, not a benchmark or scoring model. There’s no reliable data on what a ‘typical’ hospital scores, and we won’t invent one — the value is in the conversation they force, not a number they produce.

Comments are closed